

Printable patient guide PDF: Print at home/office (Letter) · PDF: Print shop (with bleed)
Overview
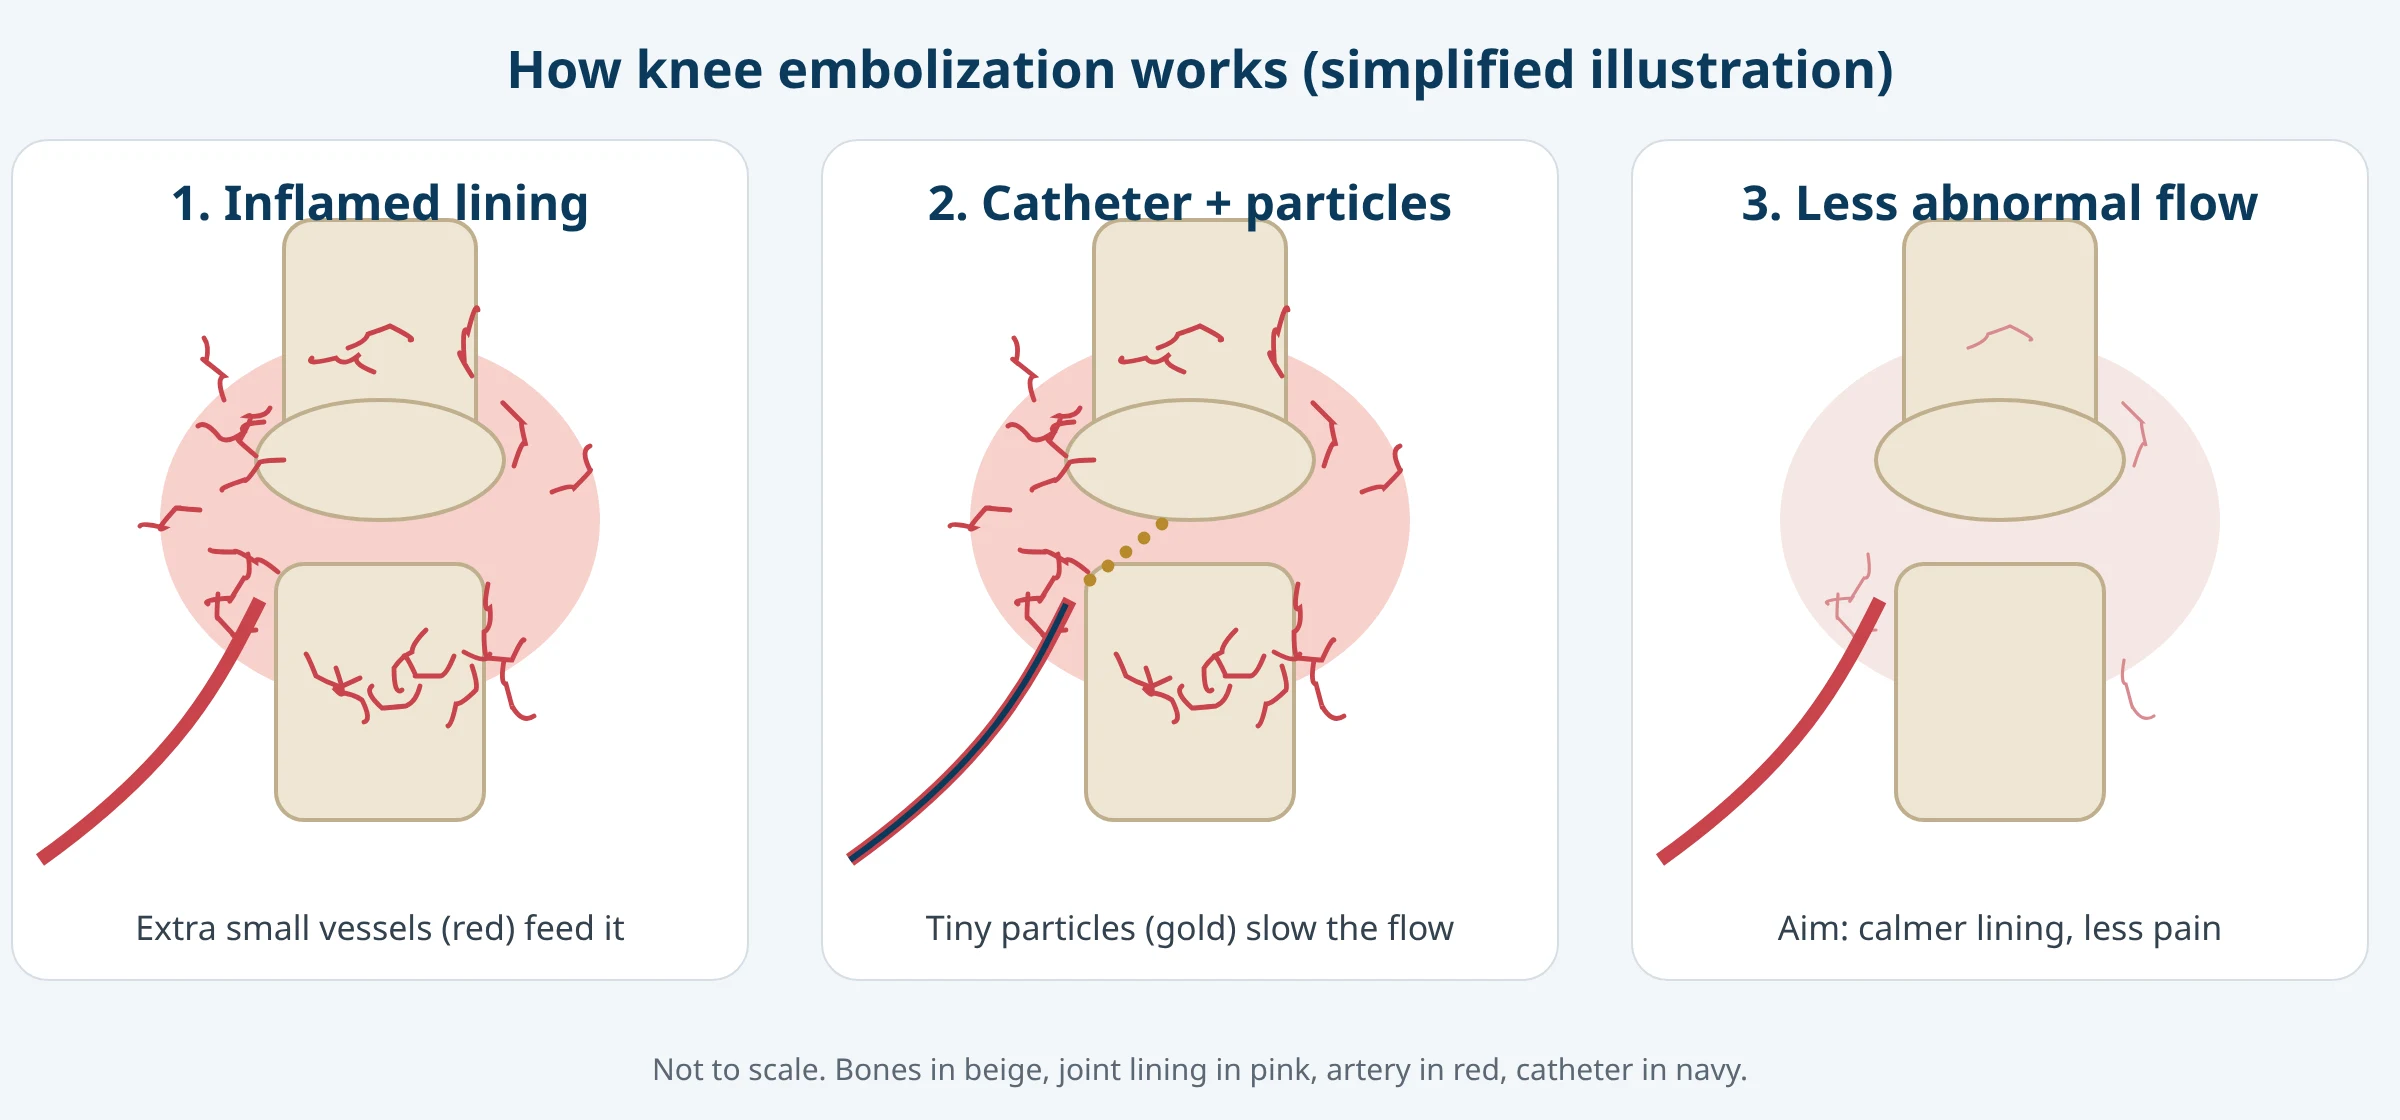
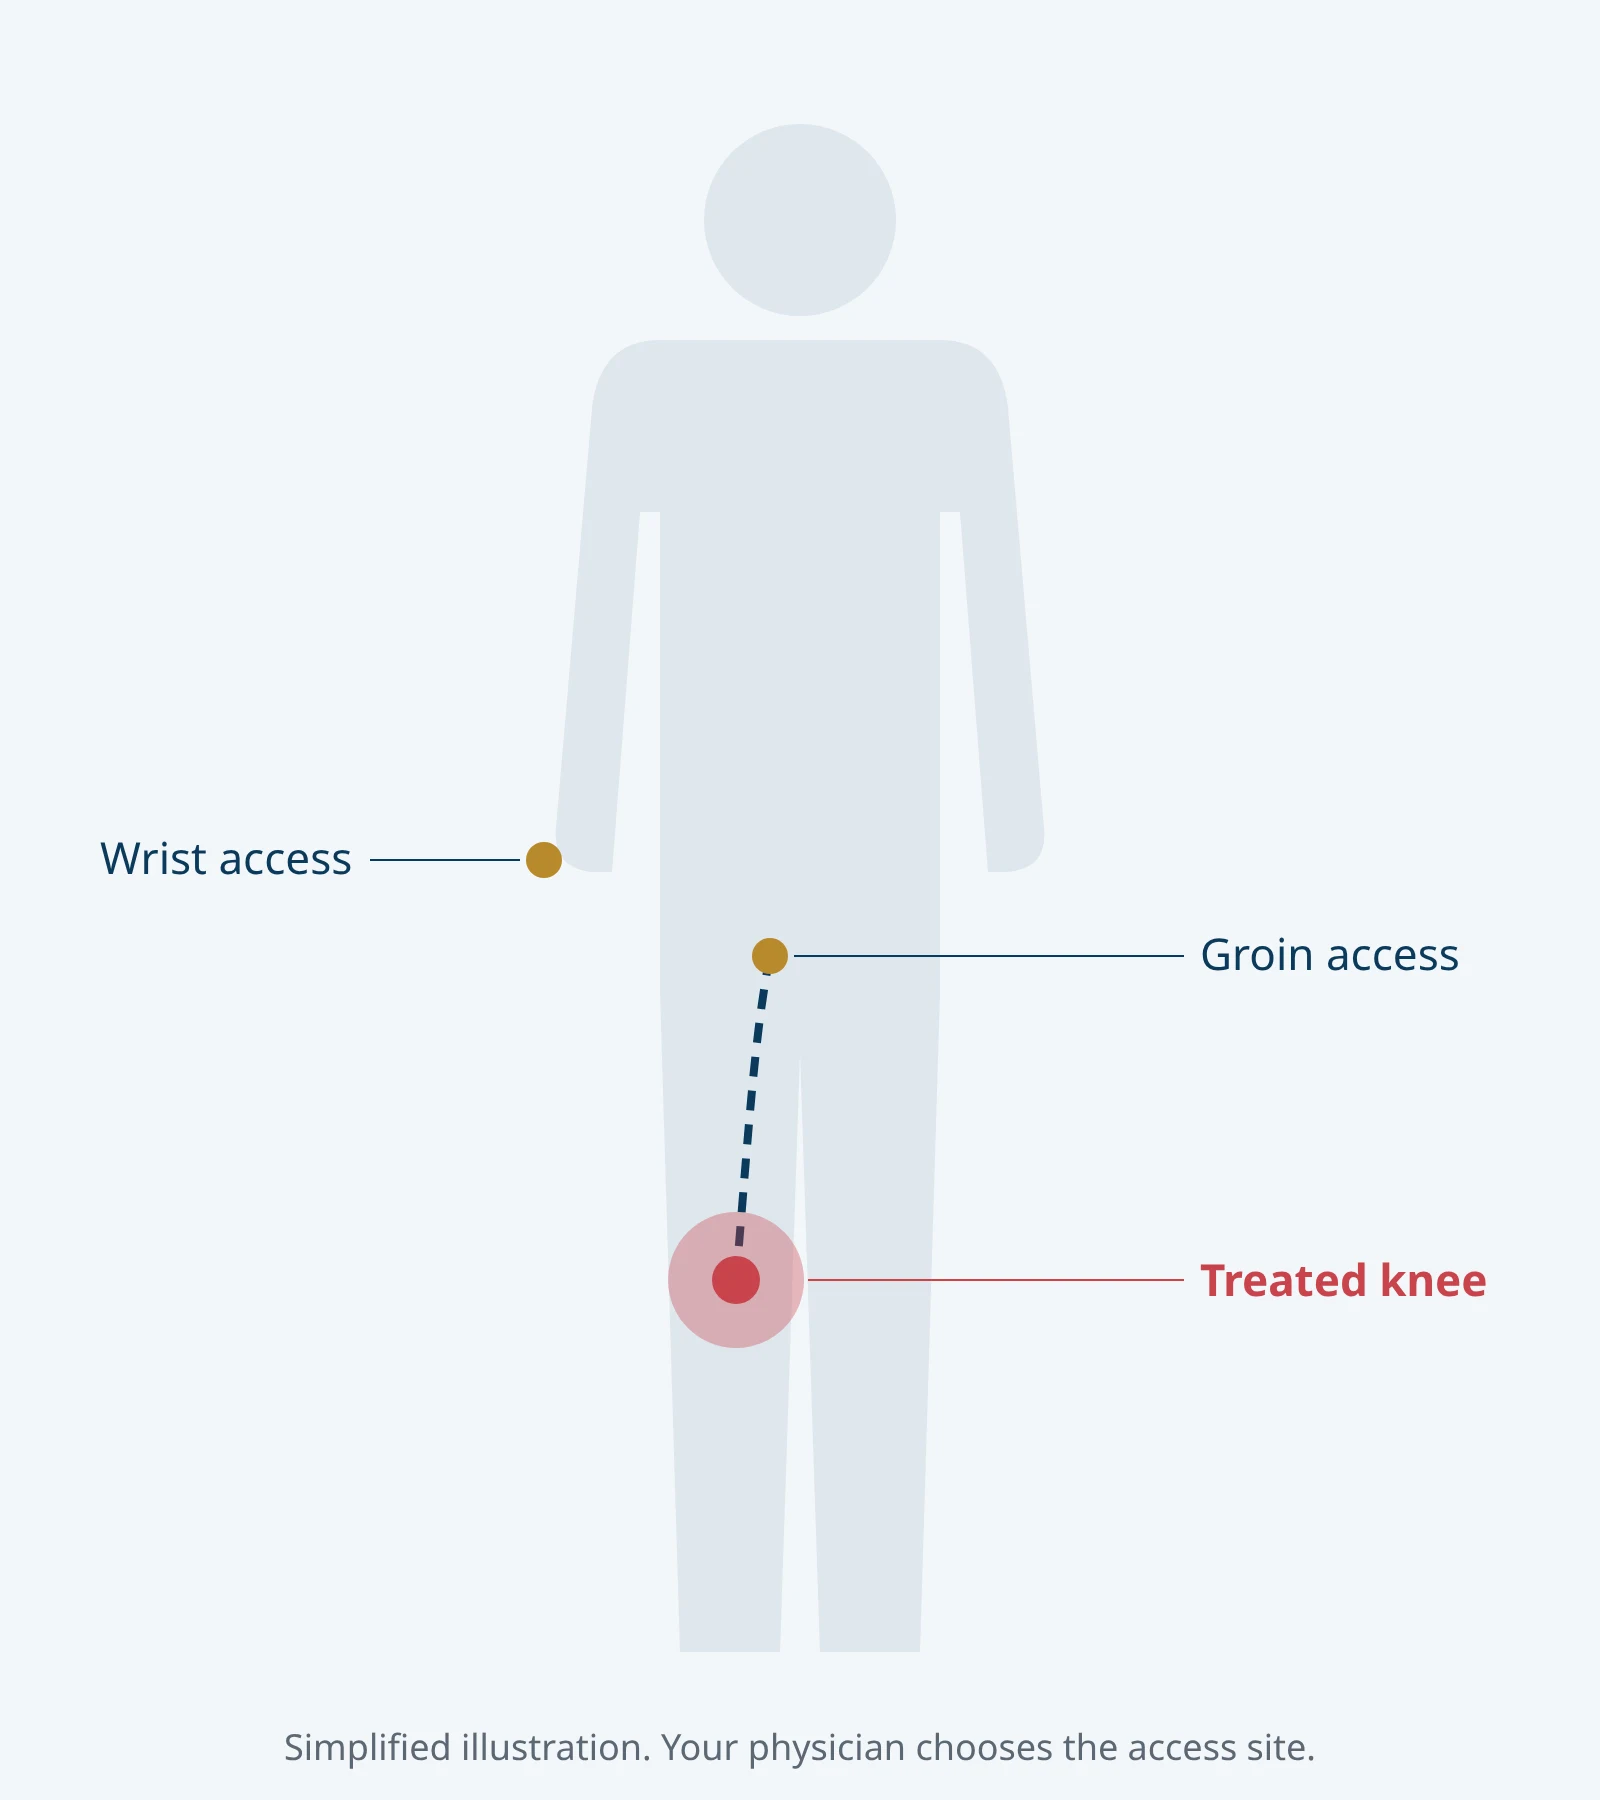
In knee arthritis, the lining of the joint (synovium) can become inflamed, and the body may grow extra small blood vessels to it. This extra blood flow is linked with swelling and pain. GAE slows that blood flow. A very thin tube (catheter) is placed at the wrist or groin and guided to the small genicular arteries around the knee, where tiny particles are released. Nothing is placed in the knee joint, and there is no cut into the knee. GAE does not repair cartilage or reverse arthritis.
GSMC providers select patients and complete the evaluation and workup at any of our 7 offices. Our team reviews long-lasting knee pain and explains every option, including whether GAE may fit. The procedure itself is performed by an interventional radiologist who works with the GSMC team, at Manchester Surgery Center (1100 Route 70 West, Whiting) or Bey Lea Surgery Center (54 Bey Lea Road, Building 2, Toms River).
Why knee pain can last: inflammation and new blood vessels
Knee osteoarthritis is more than worn cartilage. The joint lining (synovium) often becomes inflamed, a process called synovitis. Inflamed tissue sends signals that lead the body to grow new, small blood vessels (neovessels) into the lining and the tissue around the joint.
Researchers have found that small sensory nerve fibers tend to grow alongside these new vessels. Together, the extra blood flow, the inflammation and the new nerve fibers are thought to add to pain, swelling and tenderness, which helps explain why two people with similar X-rays can have very different pain.
Genicular artery embolization targets that abnormal blood flow. The genicular arteries are the small branches that supply the knee. Slowing the flow in the abnormal branches aims to calm the inflammation and the pain signals that come with it. It does not change the bones or cartilage you see on an X-ray.
Who may be a candidate
GAE may help people who have:
- Moderate to severe knee osteoarthritis pain for 3 months or more
- Pain that has not improved enough with exercise, physical therapy, weight management, medicines or knee injections
- People who want to avoid or delay knee replacement, or who are not candidates for it
- Pain that limits walking, stairs, sleep or daily tasks
Your history, exam and imaging help decide whether it fits you. Results vary.
Who may not be a good fit
Embolization may not be right for people with:
- Infection in or near the knee
- A knee replacement in the same knee (needs a separate evaluation)
- Knee pain mainly from another cause, such as a meniscus tear, the hip or the spine
- Serious kidney disease or a severe allergy to contrast dye
- A bleeding problem or severe artery disease in the leg
- Pregnancy
If another cause of pain is found, we will explain other options or coordinate a referral.
Your evaluation at any GSMC office
GSMC providers select patients and complete the evaluation and workup at any of our 7 offices, so you can start at the office closest to you. Your visit typically includes:
- A review of your symptoms, how long they have lasted and what you have already tried
- A physical exam of the knee, and of nearby areas that can refer pain (such as the hip and spine)
- A review of recent X-rays, and MRI or ultrasound if needed
- Blood work to check kidney function, if needed, because the procedure uses contrast dye
- A review of medicines, especially blood thinners, and allergies
- An honest talk about all of your options, expected results, risks and insurance coverage
Procedure day, step by step
The procedure is done as an outpatient at Manchester Surgery Center (1100 Route 70 West, Whiting) or Bey Lea Surgery Center (54 Bey Lea Road, Building 2, Toms River) by an interventional radiologist who works with the GSMC team.
- Check-in: Arrive at the time given, with your driver. Follow the eating and medicine instructions we give you.
- Preparation: A nurse reviews your health, places an IV and checks your vital signs.
- Sedation and numbing: You usually receive light sedation. The skin at the wrist or groin is numbed.
- Access: A very thin catheter is placed into an artery through a small opening.
- Mapping: Using live X-ray and contrast dye, the catheter is guided to the small arteries around the knee and the abnormal vessels are found.
- Embolization: Tiny particles are released into the target branches to slow the abnormal flow.
- Finish: The catheter is removed and pressure or a closure device is used. The procedure often takes about 1 to 2 hours.
- Recovery room: You rest while the team monitors you and the access site, then you go home the same day with written instructions.
Recovery timeline
| When | What to expect |
|---|---|
| Procedure day | Rest and monitoring after the procedure, then home with a driver. Keep the access site dry and covered; rest the arm or leg used. |
| Days 1-7 | Light walking and daily tasks are usually fine. Avoid heavy lifting, hard exercise and soaking in a tub or pool with the access site. Mild soreness in the joint or a bruise at the wrist or groin is common. |
| Weeks 2-6 | Most people are back to normal activities. Some notice pain starting to ease; for others, change is slower. Some people see a short-term skin color change over the joint that usually fades. Keep up with exercise or physical therapy. |
| About 3 months | A follow-up visit to review pain, function and goals. If embolization did not help enough, we talk through next options. |
Risks, explained
Every procedure has risks. Here is what they mean in plain language:
| Risk | What it means |
|---|---|
| Access site bruising or bleeding | A bruise or small lump at the wrist or groin is common and usually fades. Larger bleeding is uncommon; pressure or a closure device is used to prevent it. |
| Skin color change over the joint | Some people notice a temporary patchy discoloration or tenderness of the skin over the joint. It usually fades over days to weeks. |
| Particles reaching an unintended area | Rarely, particles can reach small vessels that were not targeted, which may irritate or injure skin or other tissue. Careful imaging during the procedure is used to lower this risk. |
| Contrast dye reactions and kidneys | The X-ray dye can cause an allergic reaction or strain the kidneys. We check your kidney function and allergies first. |
| Infection | Uncommon. Keep the access site clean and call us for fever or redness. |
| No improvement | Pain may not improve, or may return over time. Embolization does not rule out other treatments later. |
Our team will review your specific risks with you before you decide.
Call us for bleeding or a growing lump at the access site, fever over 101°F, a cold, pale or numb hand or foot, or skin over the joint that becomes dark, blistered or open. Call 911 for chest pain or trouble breathing.
How it compares with other options
Embolization is one option among several. Many people use more than one over time.
| Option | How it works | Good to know |
|---|---|---|
| Exercise and physical therapy | Strength, motion and walking tolerance | First-line for nearly everyone; continues after any procedure |
| Steroid injection | Short-term reduction of joint inflammation | Quick and in-office; relief is often temporary |
| Hyaluronic acid (gel) injection | Joint lubrication | Coverage and results vary |
| PRP injection | Uses your own platelets | Usually self-pay; evidence still developing |
| Genicular nerve radiofrequency ablation (RFA) | Heat calms the nerves that carry knee pain signals | Outpatient, needle-based; relief can last months; may be repeated |
| Genicular artery embolization (GAE) | Reduces abnormal blood flow linked with inflammation | Catheter-based; mixed research results; coverage varies |
| Knee replacement | Replaces the worn joint surfaces | A surgical option an orthopedic surgeon may discuss; we can coordinate a referral |
What the research shows
GAE has been studied more than embolization for other joints, and the results are mixed. Here is a plain summary of selected published studies:
- A small sham-controlled trial (Bagla and colleagues, Journal of Vascular and Interventional Radiology, 2022) of 21 people with mild to moderate knee osteoarthritis found greater pain and function improvement with GAE than with a sham (placebo) procedure at 1 month, with only minor side effects reported.
- A larger double-blind sham-controlled trial (van Zadelhoff and colleagues, BMJ Open, 2024) of 58 people with mild to moderate knee osteoarthritis found that pain improved by a similar amount with GAE and with a sham procedure at 4 months. No serious side effects occurred.
- A triple-blind trial in early-stage knee osteoarthritis (Landers and colleagues, Bone & Joint Open, 2023) of 59 people found no significant difference overall between GAE and a sham procedure at 12 months. Both groups improved. The authors said more studies are needed.
- A 2-year follow-up study without a comparison group (GENESIS, Little and colleagues, Cardiovascular and Interventional Radiology, 2024) of 46 people reported lower pain scores at 2 years. Short-term skin color changes were the most common side effect.
- The Society of Interventional Radiology published a position statement on GAE in 2026 reviewing the science, the evidence, safety and the regulatory picture.
What this means for you: GAE may help some people, but not everyone, and part of the improvement seen in studies may come from the placebo effect. Our team will talk this through with you honestly.
Sources are listed in our referring physician guide and include peer-reviewed studies found on PubMed.
Insurance and cost
Coverage for embolization varies. Many insurers consider genicular artery embolization, and embolization for the shoulder or hip, investigational, so it may not be covered. Our team will check your plan and talk with you about costs before anything is scheduled.
- Our team checks your benefits and whether prior authorization is needed before anything is scheduled.
- If your plan does not cover it, we will explain the self-pay cost in writing before you decide.
- Covered alternatives, such as physical therapy, injections or nerve ablation, are always discussed.
Call 732-202-3000 to verify your benefits. See accepted insurance.
Frequently asked questions
Is GAE surgery?
No. It is a minimally invasive procedure done through a thin catheter at the wrist or groin. There is no cut into the knee.
Does it fix the knee?
No. It does not repair cartilage. It aims to reduce the abnormal blood flow linked with inflammation and pain.
How soon might I feel a change?
If it helps, the change often builds over several weeks. Results vary, and some people notice little or no change.
Will I stay overnight?
Most people go home the same day after a period of rest and monitoring. Plan to have a driver.
Can I still have other treatments later?
Yes. Embolization does not rule out physical therapy, injections or joint replacement later.
Does insurance cover it?
Coverage for embolization varies. Many insurers consider genicular artery embolization, and embolization for the shoulder or hip, investigational, so it may not be covered. Our team will check your plan and talk with you about costs before anything is scheduled.
Who is a good candidate for GAE?
Adults with moderate to severe knee osteoarthritis pain for at least 3 months that has not improved enough with therapy, medicines or injections, especially people who want to avoid or delay knee replacement or are not candidates for it.
Does GAE hurt?
You usually get light sedation and numbing medicine at the access site. Some people feel brief warmth or discomfort during the procedure and soreness in the knee for a few days after.
How long does GAE last?
Studies have followed people for 1 to 2 years. Some people report lasting improvement, and others notice little change. There's no guarantee of how long any benefit will last.
Can GAE be done on both knees?
Sometimes. Our team will discuss whether to treat one knee at a time.
How is GAE different from a knee injection?
An injection puts medicine into the joint and usually gives temporary relief. GAE works through the arteries to reduce abnormal blood flow to the joint lining.
Where is the procedure done?
Evaluation and workup take place at any of our 7 offices. The procedure is done as an outpatient at Manchester Surgery Center in Whiting or Bey Lea Surgery Center in Toms River by an interventional radiologist who works with the GSMC team.
What should I bring to my consultation?
Your X-ray or MRI reports or images, a list of your medicines (including blood thinners), any allergies, and your insurance card.
Who performs the procedure
Where to schedule a consultation
Consultations are available at all 7 GSMC offices. Procedures are performed at Manchester Surgery Center (1100 Route 70 West, Whiting) or Bey Lea Surgery Center (54 Bey Lea Road, Building 2, Toms River).
- Whiting1100 NJ-70, Entrance B, Whiting, NJ 08759732-202-3000
- Toms River1314 Hooper Ave, 1st Floor, Toms River, NJ 08753732-202-3000
- Brick1608 NJ-88, Suite 102, Brick Township, NJ 08724732-202-3000
- Barnegat249 S Main St, Suite 5, Barnegat Township, NJ 08005732-202-3000
- Manahawkin1109 Beacon Ave, Manahawkin, NJ 08050732-202-3000
- Freehold322 Professional View Dr, 300 Building, 2nd Floor, Freehold, NJ 07728732-202-3000
- West Long Branch100 NJ-36, Suite 1K, West Long Branch, NJ 07764732-202-3000
Request a consultation
Bring a list of your medicines and any recent X-rays or MRI reports.
This page is general patient education and does not replace advice from your own clinician. Individual results vary, and no outcome can be promised. Insurance coverage varies.