
Printable patient guide PDF: Print at home/office (Letter) · PDF: Print shop (with bleed)
Overview
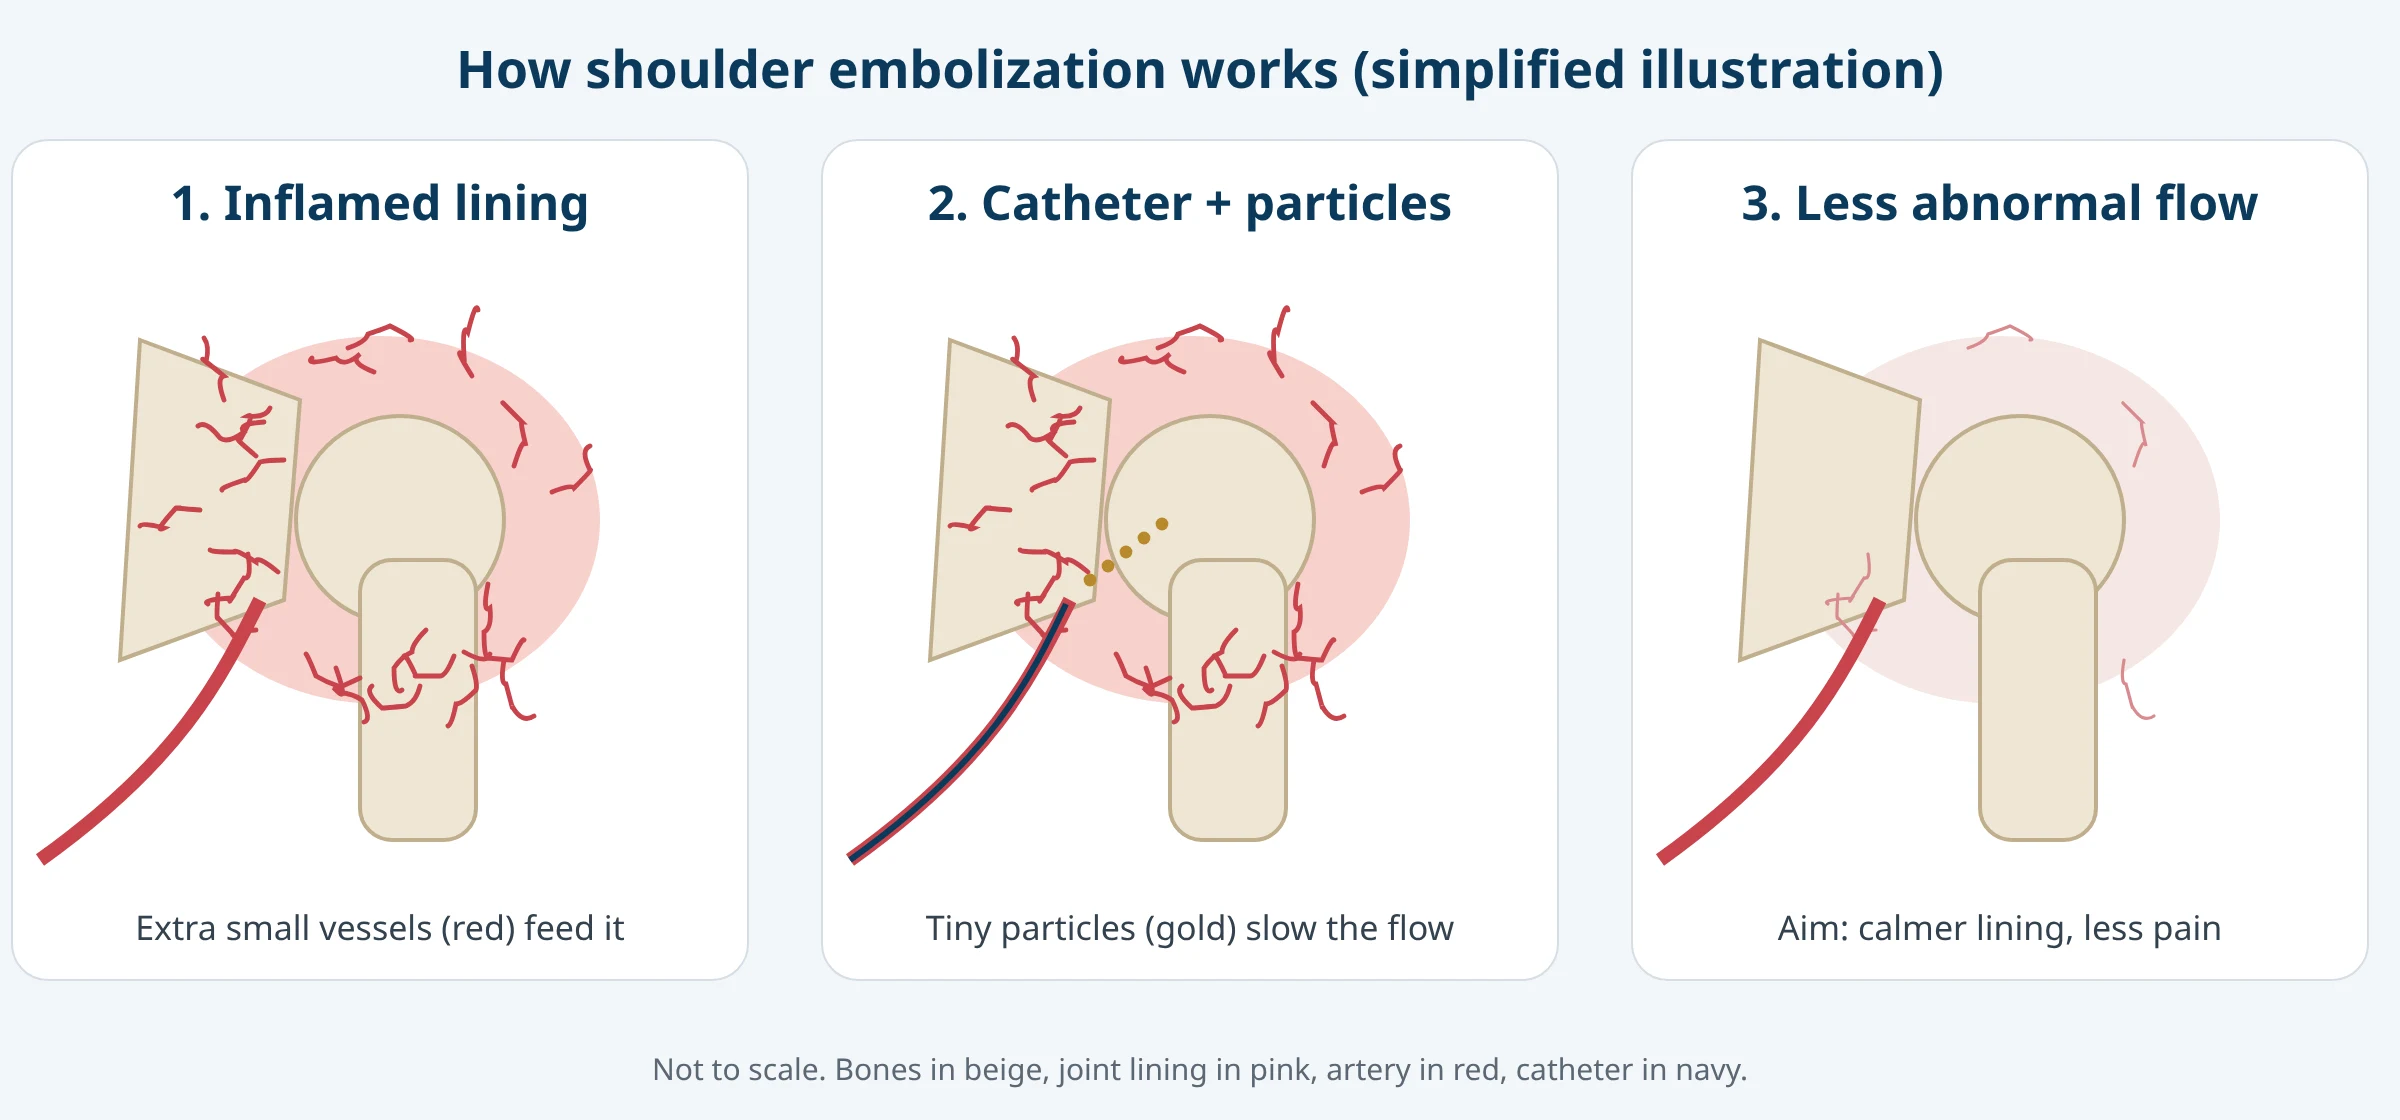
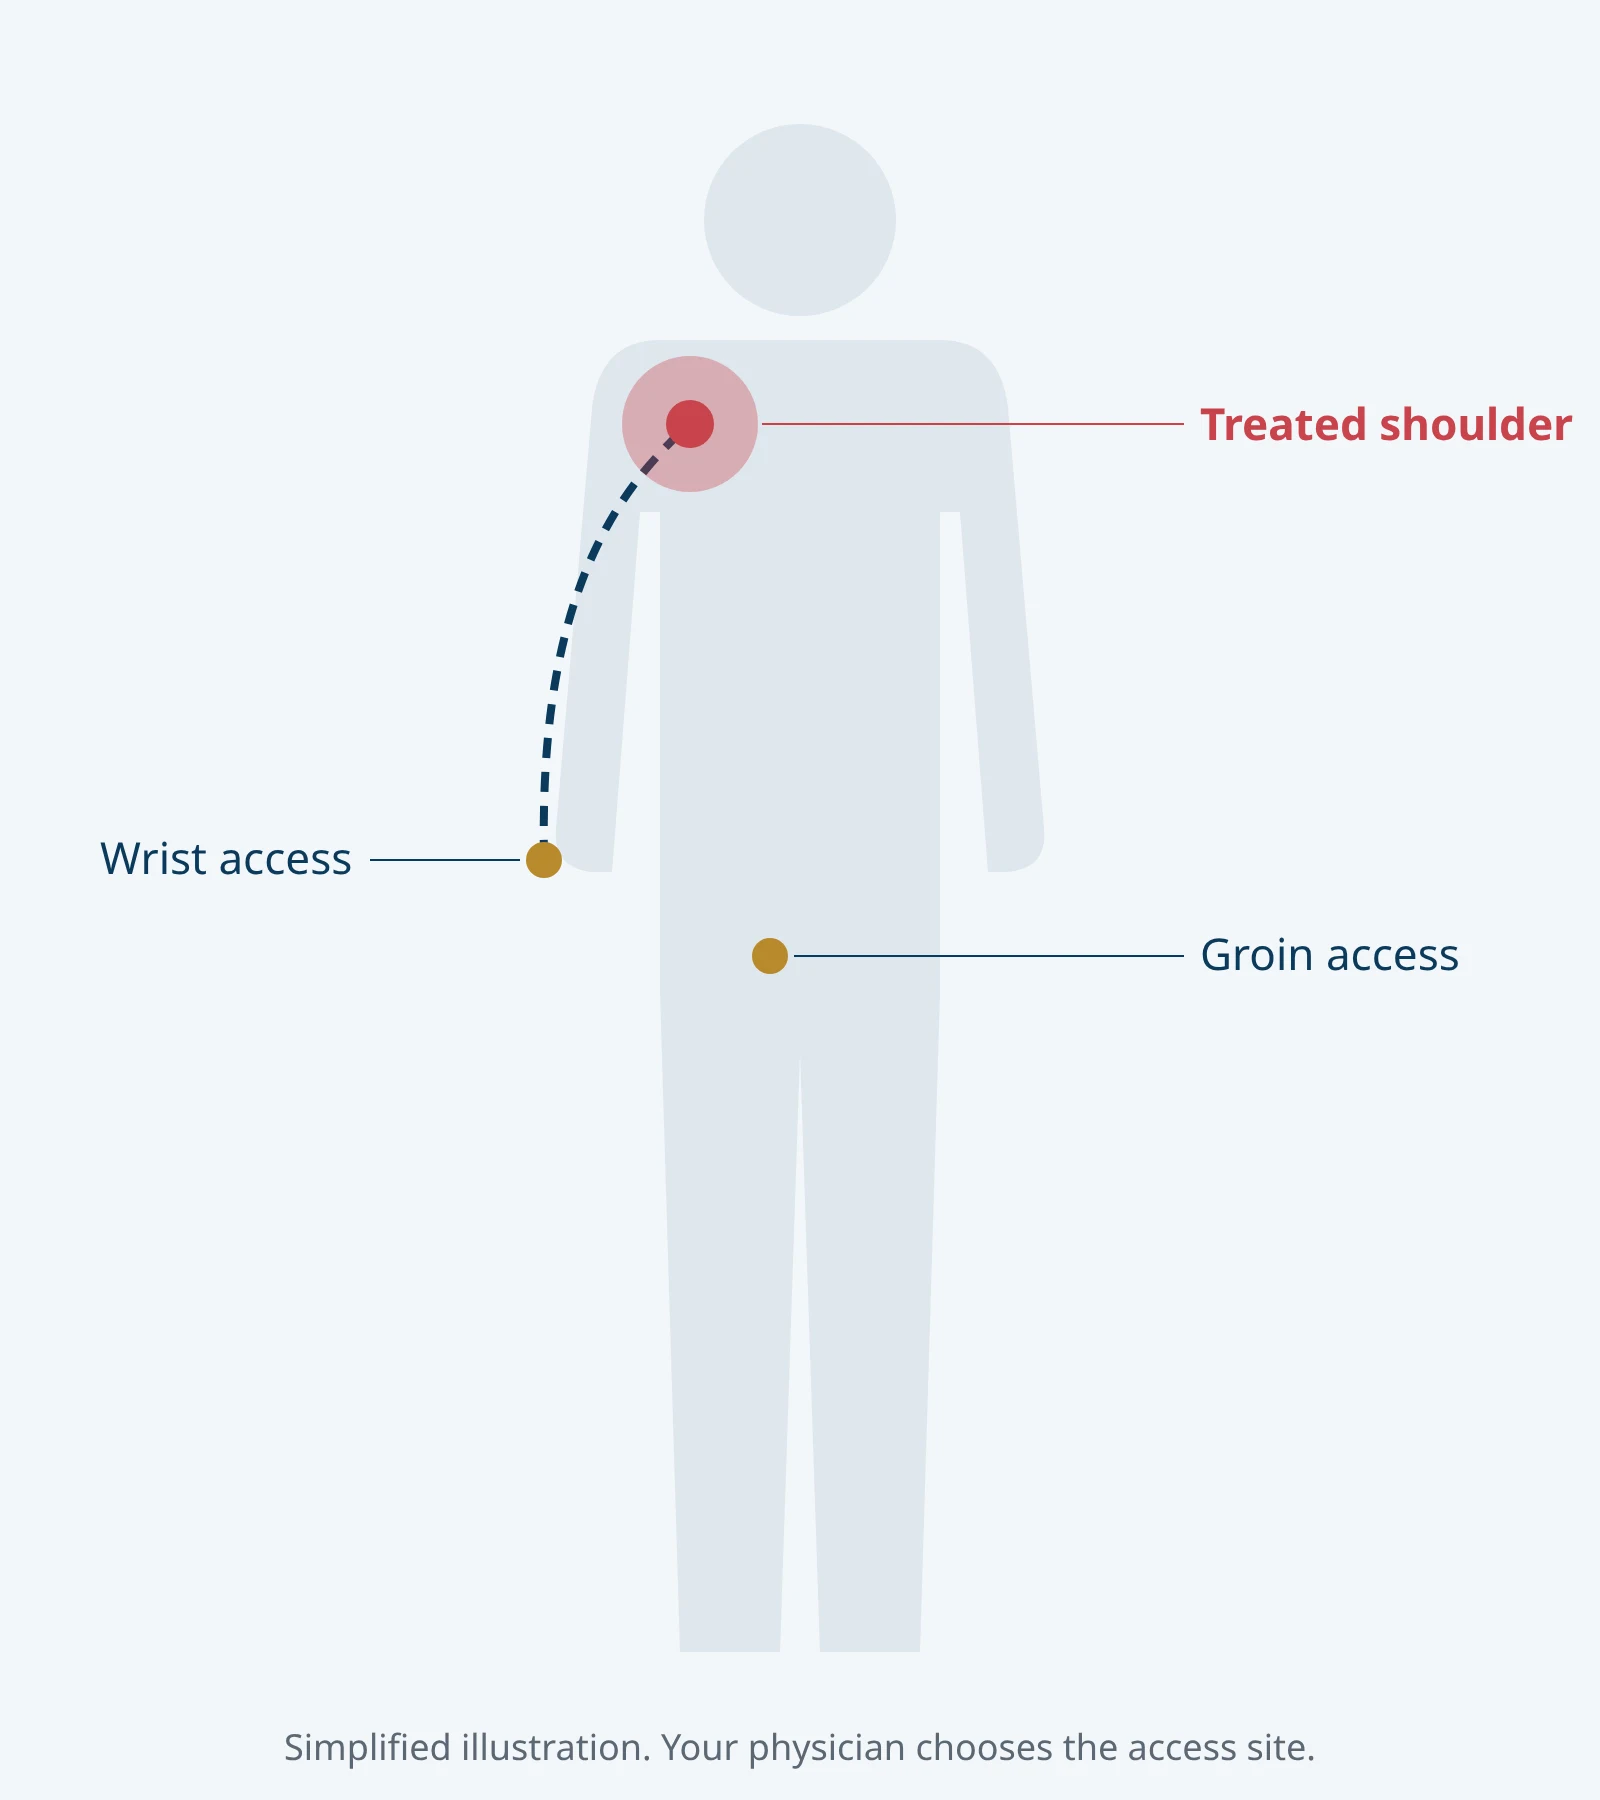
With frozen shoulder (adhesive capsulitis) and some other long-lasting shoulder problems, the tissue around the joint can become inflamed and grow extra small blood vessels. This extra blood flow is linked with pain, especially at night. Shoulder embolization slows that blood flow. A very thin tube (catheter) is placed at the wrist or groin and guided to the small arteries around the shoulder, where tiny particles are released. There is no cut into the shoulder. It does not repair a torn tendon.
GSMC providers select patients and complete the evaluation and workup at any of our 7 offices. Our team reviews long-lasting shoulder pain and explains every option, including whether shoulder embolization may fit. The procedure itself is performed by Dr. Douglas Gibbens, an interventional radiologist who works with our team, at Manchester Surgery Center (1100 Route 70 West, Whiting) or Bey Lea Surgery Center (54 Bey Lea Road, Building 2, Toms River).
Why shoulder pain can last: inflammation and new blood vessels
Frozen shoulder (adhesive capsulitis) happens when the capsule around the shoulder joint becomes inflamed, then thick and tight. It often goes through phases: a painful 'freezing' phase, a stiff 'frozen' phase, and a slow 'thawing' phase that can take many months.
During the painful phase, imaging studies have shown extra small blood vessels (neovessels) in the inflamed capsule and the tissue around the rotator interval. Sensory nerve fibers tend to grow alongside them, which is thought to add to the deep, aching pain that is often worse at night.
Shoulder embolization slows the abnormal blood flow to those areas. The goal is to ease pain so that sleep improves and stretching and physical therapy become easier to do. Some chronic shoulder pain from tendon inflammation shows a similar pattern of extra vessels, and may be evaluated for the same approach.
Who may be a candidate
Shoulder embolization may help people who have:
- Frozen shoulder (adhesive capsulitis) with pain that has lasted 3 months or more
- Shoulder pain, often worse at night, that has not improved with physical therapy, medicines or injections
- Some chronic shoulder pain from tendon inflammation, after an evaluation
- People who want to avoid or delay surgery, or who are not candidates for it
Your history, exam and imaging help decide whether it fits you. Results vary.
Who may not be a good fit
Embolization may not be right for people with:
- Infection in or near the shoulder
- A large or full-thickness rotator cuff tear that may need a surgical evaluation
- Pain mainly from the neck or another source
- Serious kidney disease or a severe allergy to contrast dye
- A bleeding problem
- Pregnancy
If another cause of pain is found, we will explain other options or coordinate a referral.
Your evaluation at any GSMC office
GSMC providers select patients and complete the evaluation and workup at any of our 7 offices, so you can start at the office closest to you. Your visit typically includes:
- A review of your symptoms, how long they have lasted and what you have already tried
- A physical exam of the shoulder, and of nearby areas that can refer pain (such as the neck)
- A review of recent X-rays, and MRI or ultrasound if needed
- Blood work to check kidney function, if needed, because the procedure uses contrast dye
- A review of medicines, especially blood thinners, and allergies
- An honest talk about all of your options, expected results, risks and insurance coverage
Procedure day, step by step
The procedure is done as an outpatient at Manchester Surgery Center (1100 Route 70 West, Whiting) or Bey Lea Surgery Center (54 Bey Lea Road, Building 2, Toms River) by Dr. Douglas Gibbens, an interventional radiologist who works with our team.
- Check-in: Arrive at the time given, with your driver. Follow the eating and medicine instructions we give you.
- Preparation: A nurse reviews your health, places an IV and checks your vital signs.
- Sedation and numbing: You usually receive light sedation. The skin at the wrist or groin is numbed.
- Access: A very thin catheter is placed into an artery through a small opening.
- Mapping: Using live X-ray and contrast dye, the catheter is guided to the small arteries around the shoulder and the abnormal vessels are found.
- Embolization: Tiny particles are released into the target branches to slow the abnormal flow.
- Finish: The catheter is removed and pressure or a closure device is used. The procedure often takes about 1 to 2 hours.
- Recovery room: You rest while the team monitors you and the access site, then you go home the same day with written instructions.
Recovery timeline
| When | What to expect |
|---|---|
| Procedure day | Rest and monitoring after the procedure, then home with a driver. Keep the access site dry and covered; rest the arm or leg used. |
| Days 1-7 | Light walking and daily tasks are usually fine. Avoid heavy lifting, hard exercise and soaking in a tub or pool with the access site. Mild soreness in the joint or a bruise at the wrist or groin is common. |
| Weeks 2-6 | Most people are back to normal activities. Some notice pain starting to ease; for others, change is slower. Some people see a short-term skin color change over the joint that usually fades. Keep up with exercise or physical therapy. |
| About 3 months | A follow-up visit to review pain, function and goals. If embolization did not help enough, we talk through next options. |
Risks, explained
Every procedure has risks. Here is what they mean in plain language:
| Risk | What it means |
|---|---|
| Access site bruising or bleeding | A bruise or small lump at the wrist or groin is common and usually fades. Larger bleeding is uncommon; pressure or a closure device is used to prevent it. |
| Skin color change over the joint | Some people notice a temporary patchy discoloration or tenderness of the skin over the joint. It usually fades over days to weeks. |
| Particles reaching an unintended area | Rarely, particles can reach small vessels that were not targeted, which may irritate or injure skin or other tissue. Careful imaging during the procedure is used to lower this risk. |
| Contrast dye reactions and kidneys | The X-ray dye can cause an allergic reaction or strain the kidneys. We check your kidney function and allergies first. |
| Infection | Uncommon. Keep the access site clean and call us for fever or redness. |
| No improvement | Pain may not improve, or may return over time. Embolization does not rule out other treatments later. |
Our team will review your specific risks with you before you decide.
Call us for bleeding or a growing lump at the access site, fever over 101°F, a cold, pale or numb hand or foot, or skin over the joint that becomes dark, blistered or open. Call 911 for chest pain or trouble breathing.
How it compares with other options
Embolization is one option among several. Many people use more than one over time.
| Option | How it works | Good to know |
|---|---|---|
| Physical therapy and home stretching | Restores motion over time | Core of frozen shoulder care at every stage |
| Steroid injection | Reduces inflammation in the joint | Often helps pain in the early phase |
| Hydrodilatation | Stretches the tight capsule with fluid | Image-guided injection |
| Suprascapular nerve block or RFA | Calms the main nerve carrying shoulder pain | Needle-based; may help pain and sleep |
| PRP injection | Uses your own platelets | Usually self-pay; evidence still developing |
| Shoulder embolization | Reduces abnormal blood flow linked with inflammation | Catheter-based; mostly uncontrolled studies; coverage varies |
| Surgical release or repair | Releases the capsule or repairs a tear | A surgical option an orthopedic surgeon may discuss |
What the research shows
Research on shoulder embolization comes mostly from studies without a comparison (sham) group, so it is less certain than research on the knee.
- An early study (Okuno and colleagues, Journal of Vascular and Interventional Radiology, 2017) followed 25 people with frozen shoulder that had not improved with other care. Pain and shoulder function scores improved over the first 6 months, and no major side effects were reported.
- A 2026 review that pooled 12 studies (Allaw and colleagues, Journal of Vascular and Interventional Radiology) covering 329 shoulders found improvements in pain, motion and function after embolization, with mostly mild side effects. The authors noted that none of the studies had a comparison group and that randomized trials are needed.
- A 2025 expert-panel review in the American Journal of Roentgenology (Sajan and colleagues) summarized embolization for musculoskeletal pain across several joints.
What this means for you: early results are encouraging, but frozen shoulder can also improve on its own over time, and studies without a comparison group can't separate the procedure's effect from natural recovery. Results vary.
Sources are listed in our referring physician guide and include peer-reviewed studies found on PubMed.
Insurance and cost
Coverage for embolization varies. Many insurers consider genicular artery embolization, and embolization for the shoulder or hip, investigational, so it may not be covered. Our team will check your plan and talk with you about costs before anything is scheduled.
- Our team checks your benefits and whether prior authorization is needed before anything is scheduled.
- If your plan does not cover it, we will explain the self-pay cost in writing before you decide.
- Covered alternatives, such as physical therapy, injections or nerve ablation, are always discussed.
Call 732-202-3000 to verify your benefits. See accepted insurance.
Frequently asked questions
Is shoulder embolization surgery?
No. It is a minimally invasive procedure done through a thin catheter at the wrist or groin. There is no cut into the shoulder.
Does it fix the shoulder?
No. It does not repair cartilage or tendons. It aims to reduce the abnormal blood flow linked with inflammation and pain.
How soon might I feel a change?
If it helps, the change often builds over several weeks. Results vary, and some people notice little or no change.
Will I stay overnight?
Most people go home the same day after a period of rest and monitoring. Plan to have a driver.
Can I still have other treatments later?
Yes. Embolization does not rule out physical therapy, injections or surgery later.
Does insurance cover it?
Coverage for embolization varies. Many insurers consider genicular artery embolization, and embolization for the shoulder or hip, investigational, so it may not be covered. Our team will check your plan and talk with you about costs before anything is scheduled.
Who is a good candidate for shoulder embolization?
Adults with frozen shoulder or chronic shoulder pain lasting at least 3 months that has not improved enough with therapy, medicines or injections, after an exam and imaging.
Will it help my shoulder move better?
The main goal is less pain. Many people find stretching and therapy easier when pain is lower, which can help motion over time.
Does it work for a rotator cuff tear?
It does not repair a tear. Large or full-thickness tears may need an orthopedic evaluation first.
Can frozen shoulder get better without treatment?
Frozen shoulder often improves slowly over many months. Embolization is considered when pain is severe or lasting despite other care.
Does shoulder embolization hurt?
You usually get light sedation and numbing medicine at the access site. Some soreness in the shoulder for a few days is common.
Where is the procedure done?
Evaluation and workup take place at any of our 7 offices. The procedure is done as an outpatient at Manchester Surgery Center in Whiting or Bey Lea Surgery Center in Toms River by Dr. Douglas Gibbens, an interventional radiologist who works with our team.
What should I bring to my consultation?
Your X-ray or MRI reports or images, a list of your medicines (including blood thinners), any allergies, and your insurance card.
Who performs the procedure
Douglas Gibbens, MD, interventional radiology
Dr. Douglas Gibbens performs embolization for GSMC patients at Manchester Surgery Center and Bey Lea Surgery Center. Evaluation, workup and follow-up are with GSMC providers at any of our 7 offices.
Where to schedule a consultation
Consultations are available at all 7 GSMC offices. Procedures are performed at Manchester Surgery Center (1100 Route 70 West, Whiting) or Bey Lea Surgery Center (54 Bey Lea Road, Building 2, Toms River).
- Whiting1100 NJ-70, Entrance B, Whiting, NJ 08759732-202-3000
- Toms River1314 Hooper Ave, 1st Floor, Toms River, NJ 08753732-202-3000
- Brick1608 NJ-88, Suite 102, Brick Township, NJ 08724732-202-3000
- Barnegat249 S Main St, Suite 5, Barnegat Township, NJ 08005732-202-3000
- Manahawkin1109 Beacon Ave, Manahawkin, NJ 08050732-202-3000
- Freehold322 Professional View Dr, 300 Building, 2nd Floor, Freehold, NJ 07728732-202-3000
- West Long Branch100 NJ-36, Suite 1K, West Long Branch, NJ 07764732-202-3000
Request a consultation
Bring a list of your medicines and any recent X-rays or MRI reports.
This page is general patient education and does not replace advice from your own clinician. Individual results vary, and no outcome can be promised. Insurance coverage varies.